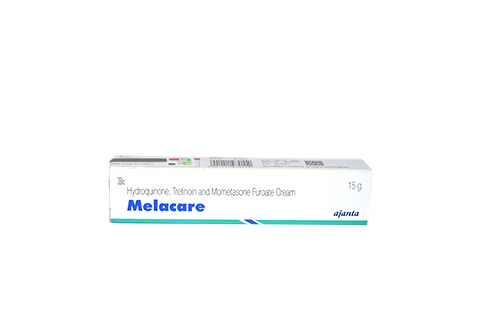
MELACARE
HYDROQUINONE TRETINOIN, MOMETASONE
What it does
Hydroquinone is a skin-lightening agent commonly used to treat dark spots and hyperpigmentation.
Commonly used for: dark spots, hyperpigmentation, melasma
Read more in plain English ↓Plain-language summary for general understanding - not medical advice. Always follow your pharmacist/doctor.
Ask about this medicine
Answers come only from this medicine's registration record, BNF monograph and interaction data - not medical advice.
Hard to find? We help patients in Kenya source rare medicines. We don't sell or dispense medicines - licensed pharmacies do.
Source this medicineRegistration & product details
Source: Pharmacy and Poisons Board · fetched 2026-01-28 22:02:58 · updated 2026-03-23 04:48:07
Drug Interactions
41Pharmacodynamic Warnings
Tretinoin appears in TABLE 5: Drugs that cause thromboembolism
Severe (2)
Mifamurtide - decreases efficacy
Corticosteroidsarepredictedtodecreasetheefficacyof mifamurtide.Avoid.rTheoretical
Vitamin - increases risk of vitamin a toxicity
TretinoinispredictedtoincreasetheriskofvitaminAtoxicity whengivenwithvitaminA.Avoid.rStudy Ribavirin e
Moderate (19)
Corticosteroids - increases exposure
Dronedarone is predicted to increase the exposure to corticosteroids (methylprednisolone). Monitor and adjust dose.
Corticosteroids - increases concentration
Miconazole is predicted to increase the concentration of corticosteroids (methylprednisolone). Monitor and adjust dose.
Corticosteroids - increases exposure
Antifungals, azoles (fluconazole, isavuconazole, posaconazole) are predicted to increase the exposure to corticosteroids (methylprednisolone). Monitor and adjust dose.
Corticosteroids - decreases exposure
Cenobamate is predicted to decrease the exposure to corticosteroids (fluticasone). Adjust dose.
Corticosteroids - decreases efficacy
Mifepristone is predicted to decrease the efficacy of corticosteroids. Use with caution and adjust dose.
Unknown (20)
Aspirin - decreases concentration
Corticosteroids are predicted to decrease the concentration of aspirin (high-dose) and aspirin (high-dose) increases the risk of gastrointestinal bleeding when given with corticosteroids.
Choline Salicylate - decreases concentration
Corticosteroids are predicted to decrease the concentration of cholinesalicylate. Ciclesonide → see corticosteroids Ciclosporin → see TABLE 2 p. 1517 (nephrotoxicity), TABLE 16 p. 1521 (increased seru
Corticosteroids - increases exposure
Cobicistat is predicted to increase the exposure to corticosteroids (beclometasone) (risk with beclometasone is likely to be lower than with other corticosteroids).
Corticosteroids - increases risk of gastrointestinal perforation
Erlotinib is predicted to increase the risk of gastrointestinal perforation when given with corticosteroids.
Corticosteroids - increases exposure
Idelalisib is predicted to increase the exposure to corticosteroids (betamethasone, budesonide, ciclesonide, deflazacort, dexamethasone, fludrocortisone, fluticasone, hydrocortisone, methylprednisolon
Data from BNF 85 (British National Formulary). This is not a substitute for professional medical advice. Matched via: class
About hydroquinone
Hydroquinone is a skin-lightening agent commonly used to treat dark spots and hyperpigmentation.
What it treats
- dark spots
- hyperpigmentation
- melasma
How it works
Hydroquinone works by reducing the amount of melanin, the pigment that gives skin its color, thereby lightening the skin in areas where there is excess pigmentation.
Who it's for
This treatment is suitable for individuals looking to lighten dark patches on their skin.
AI-assisted summary grounded in BNF data - general information only, not medical advice. Always confirm with your pharmacist or doctor.
About mometasone
Mometasone is a corticosteroid used to reduce inflammation and treat various allergic and skin conditions.
What it treats
- allergic rhinitis (hay fever)
- asthma
- skin conditions like eczema and psoriasis
How it works
It works by reducing inflammation in the body, which helps relieve symptoms.
Who it's for
It is for people suffering from allergies, asthma, or certain skin problems.
Drug class
Corticosteroids
AI-assisted summary grounded in BNF data - general information only, not medical advice. Always confirm with your pharmacist or doctor.
About tretinoin
Tretinoin is a medication used to treat acne and certain skin conditions by promoting skin cell turnover.
What it treats
- acne
- acne vulgaris
- sun-damaged skin
- certain types of skin cancer
How it works
Tretinoin helps to unclog pores and reduce the formation of acne by speeding up the growth of new skin cells.
Who it's for
This medication is suitable for individuals suffering from acne or specific skin issues.
Cautions
- • Be cautious if taking other medications that may cause blood clots.
AI-assisted summary grounded in BNF data - general information only, not medical advice. Always confirm with your pharmacist or doctor.
Clinical monograph: Tretinoin
BNF-referencedTretinoin, also known as all-trans retinoic acid, is a derivative of vitamin A used primarily in the treatment of skin conditions such as acne vulgaris and in the management of acute promyelocytic leukemia (APL). It functions by promoting cell turnover and differentiation, which aids in normalizing the growth and differentiation of skin cells and leukemic cells. Its applications extend to dermatological and oncological uses due to its cytotoxic properties against certain malignancies.
Indications
- Acne vulgaris
- Acute promyelocytic leukemia (APL)
- Cytotoxic responsive malignancies
Dosage
Children: For children, consult local protocols or BNF for Children for specific dosing regimens.
Adults: For acute promyelocytic leukemia, the recommended dose is 45 mg/m2 daily in two divided doses for a maximum duration of 90 days.
Mechanism of action
Tretinoin exerts its pharmacological effects by binding to and activating retinoic acid receptors (RARs) and retinoid X receptors (RXRs) in the nucleus. This binding induces transcriptional regulation of genes involved in cell differentiation and proliferation. In skin conditions, it enhances keratinocyte turnover and reduces inflammation, while in APL, it promotes differentiation of leukemic cells.
Pharmacodynamics
Tretinoin promotes cell production, proliferation, and differentiation, primarily affecting epidermal cells. Topically, it regulates epidermal turnover and collagen synthesis, thereby preventing collagen degradation and enhancing skin appearance. It also exhibits antineoplastic effects by inducing cytodifferentiation in tumor cells, particularly in APL, leading to decreased proliferation of leukemic cells.
Pharmacokinetics
Tretinoin is well absorbed after oral administration, with peak plasma concentrations occurring within 1-2 hours. It is extensively metabolized in the liver, primarily through oxidation and conjugation, yielding several active and inactive metabolites. The elimination half-life ranges from 0.5 to 2 hours, and its metabolites are excreted in urine. The pharmacokinetics may be affected by liver function, necessitating caution in hepatic impairment.
Contra-indications
- Pregnancy
- Breastfeeding
- Hypersensitivity to tretinoin
- History of depression or severe neuropsychiatric reactions
Adverse effects
- Headache
- Dizziness
- Nausea
- Vomiting
- Abdominal pain
- Dry skin
- Erythema
- Chills
- Insomnia
- Intracranial hypertension
- Visual impairment
- Emotional lability
- Increased risk of thromboembolism
- Hypercalcemia
- Tinnitus
- Skin reactions
Interactions
- Tretinoin and vitamin A: Severe (increases risk of vitamin A toxicity)
- Tretinoin and posaconazole: Moderate (increases risk of tretinoin toxicity)
Precautions
- Caution in hepatic impairment
- Monitor haematological and coagulation profile, liver function, serum calcium, and plasma lipids before and during treatment
- Risk of neuropsychiatric reactions; advise patients to seek medical attention for mood changes
Pregnancy
Tretinoin is teratogenic; avoid use during pregnancy.
Breast-feeding
Avoid; discontinue breastfeeding during treatment.
Storage
Store in a cool, dry place away from direct sunlight.
Formulations
- Capsules (75 mg)
- Solution for injection
- Topical formulations (cream or gel)
AI-synthesized from BNF references - general information only, not a substitute for professional medical advice or the current BNF. Verify doses with a pharmacist.
Clinical monograph: Mometasonefuroate
BNF-referencedMometasone furoate is a potent corticosteroid used primarily for the management of asthma, allergic rhinitis, and nasal polyps. It exhibits anti-inflammatory, antipruritic, and vasoconstrictive properties, making it effective in reducing airway inflammation and alleviating symptoms of nasal congestion. Mometasone furoate is typically administered via inhalation or as a nasal spray, allowing for targeted delivery and minimizing systemic side effects.
Indications
- Management of asthma in adults and adolescents not adequately controlled with inhaled corticosteroids and short-acting beta-2 agonists
- Allergic rhinitis
- Nasal polyps
Dosage
Children: For children aged 12-17 years, initially 400 micrograms daily in 1-2 divided doses, single dose to be inhaled in the evening, reduced to 200 micrograms once daily if control is maintained.
Adults: 1 inhalation once daily; dosage may be increased to 400 micrograms twice daily if necessary.
Mechanism of action
Mometasone furoate works by binding to glucocorticoid receptors, leading to the modulation of gene expression. This results in the inhibition of pro-inflammatory cytokines and chemokines, thereby reducing inflammation in the airways and nasal passages. It also inhibits the activation of inflammatory cells such as eosinophils and mast cells, contributing to its therapeutic effects.
Pharmacodynamics
As a corticosteroid, mometasone furoate exhibits significant anti-inflammatory effects, which are crucial in the management of asthma and allergic conditions. The drug reduces airway hyper-responsiveness and decreases mucus production, leading to improved airflow and decreased symptoms such as wheezing and shortness of breath. Its rapid onset of action is beneficial for acute symptom relief.
Pharmacokinetics
Mometasone furoate is well-absorbed when administered by inhalation or nasal spray. It undergoes extensive first-pass metabolism in the liver, resulting in low systemic bioavailability. The drug is primarily excreted via the feces, with a small percentage eliminated through the urine. The half-life of mometasone furoate is approximately 5.8 hours, allowing for once-daily dosing in many cases.
Adverse effects
- Candida infection
- Nasal ulceration
- Throat irritation
- Headache
- Cough
Interactions
- Corticosteroids
- Beta2 agonists
Precautions
- Use with caution in patients with active or quiescent tuberculosis infections
- Monitor for signs of infection
- Use in hepatic impairment requires caution
Pregnancy
Use only if potential benefit outweighs risk-limited information available.
Breast-feeding
Avoid-present in milk in animal studies.
Storage
Store below 30°C. Protect from light and moisture.
Formulations
- {'form': 'Inhalation powder', 'strength': '200 micrograms per dose', 'brand': 'Asmanex Twisthaler'}
- {'form': 'Aqueous nasal spray', 'strength': '50 micrograms per dose', 'brand': 'Flixonase'}
AI-synthesized from BNF references - general information only, not a substitute for professional medical advice or the current BNF. Verify doses with a pharmacist.
Clinical monograph: hydroquinone
BNF-referencedHydroquinone is a skin-lightening agent commonly used in cosmetic formulations to treat conditions associated with hyperpigmentation, such as melasma, age spots, and post-inflammatory hyperpigmentation. It functions primarily by inhibiting the enzyme tyrosinase, which is crucial for melanin production in the skin. The therapeutic effects of hydroquinone typically develop over several months of consistent use.
Indications
- Hyperpigmentation
- Melasma
- Post-inflammatory hyperpigmentation
- Age spots
Dosage
Children: Refer to the BNF for Children for appropriate dosing information, as pediatric dosing may differ significantly from adult recommendations.
Adults: Topical application of hydroquinone is typically applied to the affected areas twice daily. Patients should follow specific product guidelines and consult healthcare professionals for individualized treatment plans.
Mechanism of action
Hydroquinone reduces melanin pigment production through inhibition of the tyrosinase enzyme, which is involved in the initial step of the melanin pigment biosynthesis pathway. This inhibition decreases the overall production of melanin, leading to a lighter skin appearance.
Pharmacodynamics
The pharmacodynamic effects of hydroquinone are largely related to its ability to modulate melanin synthesis in melanocytes by inhibiting tyrosinase activity. Prolonged exposure to hydroquinone can lead to a gradual lightening of the skin. However, the drug's efficacy may vary among individuals based on skin type and the extent of hyperpigmentation.
Pharmacokinetics
Hydroquinone is absorbed through the skin, reaching systemic circulation to some extent. The metabolic pathways of hydroquinone include its conversion to various reactive metabolites, which can generate reactive oxygen species and may lead to oxidative stress. Hydroquinone has a half-life that varies based on the route of administration and individual metabolism, but specific pharmacokinetic parameters are not well defined in the literature.
Adverse effects
- Skin irritation
- Erythema
- Hypopigmentation
- Allergic contact dermatitis
Precautions
- Use with caution in individuals with a history of skin sensitivity or allergy
- Avoid prolonged exposure to sunlight or ultraviolet light during treatment
- Not for use on broken or inflamed skin
Pregnancy
Hydroquinone should be used during pregnancy only if clearly needed, as safety in pregnancy has not been established.
Breast-feeding
Caution is advised when using hydroquinone while breastfeeding, as it is not known whether it is excreted in human milk.
Storage
Store at room temperature, away from light and moisture. Keep out of reach of children.
Formulations
- Cream
- Gel
- Lotion
AI-synthesized from BNF references - general information only, not a substitute for professional medical advice or the current BNF. Verify doses with a pharmacist.
Clinical monograph: mometasone
BNF-referencedMometasone is a synthetic corticosteroid that exhibits medium potency and is primarily used for its anti-inflammatory, antipruritic, and vasoconstrictive properties. It is effective in the management of various inflammatory conditions, such as asthma, allergic rhinitis, and skin disorders. Mometasone works by reducing inflammation and suppressing immune responses, providing relief from symptoms associated with these conditions.
Indications
- Asthma
- Allergic rhinitis
- Skin conditions (e.g., eczema, dermatitis)
Dosage
Children: Refer to the BNF for Children for appropriate paediatric dosing guidelines.
Adults: Refer to the specific BNF guidelines for adult dosing, which may vary based on the condition being treated.
Mechanism of action
Mometasone exerts its anti-inflammatory effects by crossing cell membranes and binding with high affinity to specific cytoplasmic glucocorticoid receptors. This interaction diminishes the release of leukocytic acid hydrolases, prevents macrophage accumulation at inflamed sites, interferes with leukocyte adhesion to capillary walls, reduces capillary membrane permeability, and inhibits the release of histamine and kinin. Additionally, mometasone inhibits the formation of scar tissue and acts through phospholipase A2 inhibitory proteins, known as lipocortins, which control the synthesis of potent inflammatory mediators like prostaglandins and leukotrienes.
Pharmacodynamics
Mometasone demonstrates medium potency as a corticosteroid, effectively reducing inflammation without significant systemic absorption due to extensive hepatic metabolism. Its local effects are favored over systemic effects, making it suitable for chronic conditions like asthma, where immediate symptom relief is not expected. The onset of action may take 1 to 2 weeks for maximum improvement in asthma symptoms following inhalation. Discontinuation of mometasone may allow for sustained asthma stability for several days.
Pharmacokinetics
Mometasone is extensively metabolized in the liver, resulting in a low systemic bioavailability. Its pharmacokinetic profile includes rapid absorption and distribution, with a half-life that supports once-daily dosing in many cases. The lack of active metabolites contributes to its safety profile, minimizing systemic effects while providing effective local action.
Interactions
- cobicistat+mometasone: Unknown (increases exposure)
- idelalisib+mometasone: Unknown (increases exposure)
- clarithromycin+mometasone: Unknown (increases exposure)
Pregnancy
Mometasone should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
Breast-feeding
Caution should be exercised when administering mometasone to nursing mothers, as it is not known whether it is excreted in human milk.
Storage
Store at room temperature, away from light and moisture. Do not freeze.
Formulations
- Mometasone furoate nasal spray
- Mometasone furoate inhalation aerosol
- Mometasone furoate cream
- Mometasone furoate ointment
- Mometasone furoate lotion
AI-synthesized from BNF references - general information only, not a substitute for professional medical advice or the current BNF. Verify doses with a pharmacist.
Molecular reference: Tretinoin
PubChem CID 444795Molecular formula: C20H28O2
Mechanism of action
The exact mechanism of action of tretinoin in skin conditions and acute promyelocytic leukemia (APL) has not been fully elucidated; however, several proposed mechanisms exist. Tretinoin is believed to exert its pharmacological actions by binding to and activating two types of nuclear receptors - retinoic acid receptors (RARs) alpha, beta, and gamma and retinoid X receptors (RXRs). In the human skin, RARs (especially RAR-alpha) form heterodimers with RXR to act as inducible transcription regulators of genes involved in cell differentiation by binding to retinoic acid response elements. Tretinoin binds to RXRs to promote epidermal proliferation. It also blocks the actions of inflammatory mediators, enhancing procollagen production and collagen type I and III formations. Some animal and human studies suggest that tretinoin induces the expression of transforming growth factor beta (TGF-β), which stimulates the transcription of several types of collagen messenger RNA. Collagen formation curtails further solar UV-induced skin damage and aging processes. Acne is associated with abnormal follicular formation from excessive keratinization of epithelial cells. Tretinoin promotes cornified cell detachment and enhances keratinocyte shedding. It also stimulates mitotic activity and loosely-adherent corneocyte turnover to expel comedo contents, reducing microcomedo precursor lesions of acne vulgaris. Tretinoin may reduce epidermal melanin and pigmentation by increasing keratinocyte turnover and reducing tyrosinase activity. RAR-alpha and -beta have also been implicated in APL. APL is characterized by a t(15;17) chromosomal translocation, which fuses the promyelocytic myeloid leukemia (PML) gene with the RAR-alpha gene. The resulting PML-RAR-alpha fusion protein plays a role in the pathogenesis of APL by aberrating promyelocyte differentiation. The PML-RAR-alpha fusion protein is found to be predominant in leukemic cells, exerting a dominant negative effect on RAR, RXR and PML function. Tretinoin induces terminal differentiation in hemopoietic precursor cell lines and APL cells. Tretinoin is believed to promote caspase-mediated cleavage and proteasome-dependent degradation to cause apoptosis and degradation of the PML-RAR-alpha fusion protein. It may also convert the fusion protein from a transcription repressor to an activator. Although the precise mechanism(s) of action of tretinoin has not been fully elucidated, it is known that the drug is not a cytolytic agent. Tretinoin induces cellular differentiation and decreases the proliferation of acute promyelocytic leukemia (APL) cells. The PML/RAR-a fusion protein resulting from the chromosomal translocation appears to block myeloid differentiation at the promyelocyte stage, possibly by complexing and inactivating wild-type PML or by inhibiting the normal retinoic acid signaling pathway. In patients with APL who achieve a complete remission with tretinoin therapy, the drug causes an initial maturation of the primitive promyelocytes derived from the cellular leukemic clone followed by a repopulation of the bone marrow and peripheral blood by normal, polyclonal hematopoietic cells. Observations supporting cellular differentiation effects as a mechanism of tretinoin include the absence of bone marrow hypoplasia during induction, the appearance of immunophenotypically unique "intermediate cells" expressing both mature and immature cell surface antigens, and the presence of both Auer rods and the translocation in morphologically mature granulocytes until a late stage of induction. The mechanism by which the population of malignant cells is eliminated is not fully understood but appears to involve apoptosis (programmed cell death). Following induction therapy, the PML/RAR-a fusion protein can be detected in the majority of patients, suggesting that tretinoin alone does not eradicate the leukemic clone.
Pharmacodynamics
Tretinoin is a vitamin A derivative that promotes cell production, proliferation, and differentiation. When used topically, tretinoin regulates epidermal cell turnover and collagen production. It also prevents collagen loss, reduces inflammation, and blocks the induction of matrix metalloproteinase (MMP), which are enzymes that disrupt collagen and elastic fibres. In short-term and long-term studies, topical application of tretinoin at doses ranging from 0.001% to 0.1% was associated with improvements in clinical signs of photoaging and fine wrinkles, increased epidermal thickness, compaction of the stratum corneum, and decreased melanin content. It also improved melanocyte differentiation and distribution, promotion of epidermal hyperplasia, and angiogenesis. Tretinoin exhibits antineoplastic activities when given orally. Tretinoin was shown to induce differentiation in tumour cells. It induced cytodifferentiation and decreased acute promyelocytic leukemia (APL) cell proliferation in culture and _in vivo_. In patients with APL, tretinoin promoted the initial maturation of the primitive promyelocytes derived from the leukemic clone, followed by a repopulation of the bone marrow and peripheral blood by normal, polyclonal hematopoietic cells in patients achieving complete remission.
Biological pathways
Source: PubChem (NCBI) · pathways from PathBank, Reactome, WikiPathways & PharmGKB.
Molecular reference: hydroquinone
PubChem CID 785Molecular formula: C6H6O2
Mechanism of action
Hydroquinone reduces melanin pigment production through inhibition of the tyrosinase enzyme, which is involved in the initial step of the melanin pigment biosynthesis pathway. Hydroquinone takes several months to take effect. Benzene is a well-established human carcinogen. Benzene metabolites hydroquinone (HQ) and benzoquinone (BQ) are highly reactive molecules capable of producing reactive oxygen species and causing oxidative stress. /This study/ investigated the role of the Nrf2, a key nuclear transcription factor that regulates antioxidant response element (ARE)-containing genes, in defense against HQ- and BQ-induced cytotoxicity in cultured human lung epithelial cells (Beas-2B). When the cells were exposed to HQ or BQ the activity of an ARE reporter was induced in a dose-dependent manner, meanwhile Nrf2 protein levels were elevated and accumulated in the nucleus. Increased expression of well-known Nrf2-dependent proteins including NQO1, GCLM, GSS and HMOX was also observed in the HQ/BQ-treated cells. Moreover, transient overexpression of Nrf2 conferred protection against HQ- and BQ-induced cell death, whereas knockdown of Nrf2 by small interfering RNA resulted in increased apoptosis. /This study/ also found that the increased susceptibility of Nrf2-knockdown cells to HQ and BQ was associated with reduced glutathione levels and loss of inducibility of ARE-driven genes, suggesting that deficiency of Nrf2 impairs cellular redox capacity to counteract oxidative damage. Altogether, these results suggest that Nrf2-ARE pathway is essential for protection against HQ- and BQ-induced toxicity.
Biological pathways
Source: PubChem (NCBI) · pathways from PathBank, Reactome, WikiPathways & PharmGKB.
Molecular reference: mometasone
PubChem CID 441335Molecular formula: C22H28Cl2O4
Mechanism of action
Unbound corticosteroids cross cell membranes and bind with high affinity to specific cytoplasmic receptors. Inflammation is decreased by diminishing the release of leukocytic acid hydrolases, prevention of macrophage accumulation at inflamed sites, interference with leukocyte adhesion to the capillary wall, reduction of capillary membrane permeability, reduction of complement components, inhibition of histamine and kinin release, and interference with the formation of scar tissue. The antiinflammatory actions of corticosteroids are thought to involve phospholipase A<sub>2</sub> inhibitory proteins, lipocortins, which control the biosynthesis of potent mediators of inflammation such as prostaglandins and leukotrienes. Mometasone furoate has been shown in vitro to exhibit a binding affinity for the human glucocorticoid receptor which is approximately 12 times that of dexamethasone, 7 times that of triamcinolone acetonide, 5 times that of budesonide, and 1.5 times that of fluticasone.
Pharmacodynamics
Mometasone is a medium-potency synthetic corticosteroid with antiinflammatory, antipruritic, and vasoconstrictive properties. Studies in asthmatic patients have demonstrated that mometasone provides a favorable ratio of topical to systemic activity due to its primary local effect along with the extensive hepatic metabolism and the lack of active metabolites. Though effective for the treatment of asthma, glucocorticoids do not affect asthma symptoms immediately. Maximum improvement in symptoms following inhaled administration of mometasone furoate may not be achieved for 1 to 2 weeks or longer after starting treatment. When glucocorticoids are discontinued, asthma stability may persist for several days or longer. Mometasone has been shown in vitro to exhibit a binding affinity for the human glucocorticoid receptor which is approximately 12 times that of dexamethasone, 7 times that of triamcinolone acetonide, 5 times that of budesonide, and 1.5 times that of fluticasone. The clinical significance of these findings is unknown.
Source: PubChem (NCBI) · pathways from PathBank, Reactome, WikiPathways & PharmGKB.
This drug in other countries
The same active ingredient registered across other registries we cover - including different brands.
- ADSONE · East African Overseas
- Acne Free · Amoun Pharmaceutical Company
- Acretin cream 0.025% · Jamjoom Pharmaceuticals
- ELOCOM CREAM · Organon
- ELOCOM Ointment · Organon
- Elica - M · Jamjoom Pharmaceuticals
- ACRETIN CREAM (Each gram contains Tretinoin 0.05%w/w) · Jamjoom Pharmaceuticals
- ACRETIN C GEL (Each 30g Aluminium collapsible tube contains Clindamycin Phosphate/Tretinoin 1.2%/0.025%) · Jamjoom Pharmaceuticals
- ACRETIN TRETINOIN (Each 30g tube contains Tretinoin 0.025%w/w) · Jamjoom Pharmaceuticals
- ACRETINC GEL (Each 30g Aluminium collapsible tube contains Clindamycin Phosphate/ tretinoin · Jamjoom Pharmaceuticals
- ADVASONE SPRAY ( MOMETASONE FUMERATE 0.52%) · Biodeal Pharmaceuticals
- DERMAV CREAM (Each tube contains Hydroquinone USP/ Tretinoin USP/ Mometasone furoate USP 2%w/v, 0.025%w/w, 0.10%w/w) · Mars Remedies
- ACNESOL 0.05%W/W CREAM
- CLEAR-T 1%/0.025%W/W GEL
- FUNBACT-A 360ML HOMOGENEOUS LIQUID
- MOMENAP_NS_0.05 0.05%W/V SUSPENSION
- RETIN-A 0.025% GEL
- RETIN-A 0.05% CREAM
- AXCEL MOMETASONE 0.1% CREAM · Kotra Pharma
- ELOCON · Organon
- MOMATE · Glenmark Pharmaceutical Ltd
- MOMATE · Glenmark Pharmaceutical Ltd
- MOMATE AZ · Glenmark Pharmaceuticals Limited
- MOMATE CREAM · Glenmark Pharmaceutical Ltd